My final day in Anaesthetics came round very quickly. I was once again in plastic surgery.
The SpR who was looking after me today also had a trainee SpR with him. We went to see a few patients and do anaesthetic assessments - one lady had a suspected ejection systolic murmur (Aortic Stenosis) and she had to have an echo before her surgery.
The actual theatre list started at 10am, and because the plastic surgeon was otherwise occupied in the morning, our theatre was helping with the trauma list. So we had a haematoma evacuation to do, and a crushed finger repair. in both cases the patients had been in for a few days and so they already had venflons in, so I couldn't practice my technique.
My supervisor said that all the Anaesthatists I had been in theatre with had been pleased with my performance and said that they had enjoyed having me as a student. he wished me the best of luck in my exams, took the Elective assessment sheet off me and sent me home about 3!
Showing posts with label theatre. Show all posts
Showing posts with label theatre. Show all posts
Wednesday, August 8, 2007


Wednesday, July 25, 2007
Elective - days five & six
Day Five - Tuesday
This morning I was in theatre with my supervisor. The first case was a very large lady, on whom there were no veins visible at the wrist or indeed anywhere on the forearms. Thus I git to see a recent development - the use of ultrasound in anaesthesia - to locate the vein before putting the cannula into the vein. All in all it meant that it took about 90 minutes just to anaesthetise the patient and get them onto the operating table. there was also an issue of whether the lady would be too heavy for the operating table.
This gave my supervisor a nice opportunity to give me a tutorial on obesity, its effects on body systems, and the difficulty it causes in operations. We then went on to cover fluid balance and blood products and transfusion.
In the afternoon, I was with another SpR and we were again doing the plastic surgery list. These cases were thankfully more straightforward - some were as short as 30 minutes. The SpR explained a bit about the different types of anaesthetic drugs and also allowed me to do my first venflon.....sticking needles into people is quite scary....and also to put some of the airway tubes in. Apparently my main problem is one common to most students - I was too gentle and didn't push the tube hard enough. My venflon was also too hesitant and I wasn't confident enough pushing it in. I assume this confidence comes with the more that you do.
Day Six - Wednesday
Today I was in the emergency / trauma theatre which deals mainly in orthopaedics. There are two trauma theatres and I got to spend time in both theatres. I spent most of the day with the Duty SHO. Two of the cases today didn't have general anaesthetic (where they are put to sleep) but instead had a local block, which again is done under ultrasound. Both cases involved hand surgery. Thus the anaesthatist had to identify the brachial plexus of nerves in the top of the arm and inject the anaesthetic there to block the impulses coming up from the pain sensors in the hand / arm. I was very surprised at how the patients were so calm, oblivious to the procedures they were undergoing which all looked painful.
The regional block method takes longer than just putting the patient to sleep under a general anaesthetic but had less side effects, and less risk than the general anaesthetic would have.
I also got to see a hip screwing in the emergency orthopaedic theatre, which was a bit more brutal than I was expecting - orthopaedic surgeons do use tools which look too much like my school woodworking workshop.
Wednesday, July 18, 2007
Elective - day 2 (maternity)

Today was my first ever visit to a labour ward. I was there to see what the anaesthetists do, although I also got to see 2 C-sections as well. It's much more umm, well, eerr, brutal than I thought. However, either way, 2 7lb babies were born fit and healthy so it can't be bad for them.
I don't know if today was a slow baby day, or if it's normally quiet, but there were only 4 ladies required anaesthetic intervention - either for a C-section, or for epidurals, so I got 3 or 4 tutorials on different aspects of anaesthetics. I got to spend time with an SHO, SpR and Consultant and got to see their different styles but also the high degree of teamwork they have.
- The difference between a spinal and an epidural anaesthetic.
- What the things to look out for when anaesthetising someone who is fit, healthy and awake.
- How they manage a patient who has an 'allergy' to one of the commonly used drugs.
 SHO Teaching & careers advice
The SHO I was with for that part of the day was really helpful at explaining why these things are important and why it is good to pick them up as a medical student, and not wait til you are a JHO. She also explained some of the simpler things about anaesthetics and the anatomy of where the different needles go. She also gave some advice on why Anaesthetics is a good choice as a career and also how to manage your FY1 choices and accepting that you are an admin clerk and spend most of your time monitoring things, checking up on things or ordering test fro other departments, She also said about knowing the patients on you ward because more senior staff are off at clinics, research etc, and it is down to you to know who slept well or didn't, whose birthday it is, whose family members are away and haven't been to see them, and things like that which help you to explain things to the consultant. Also getting to know some patient history and circumstances is important.
 Seeing tomorrows patients
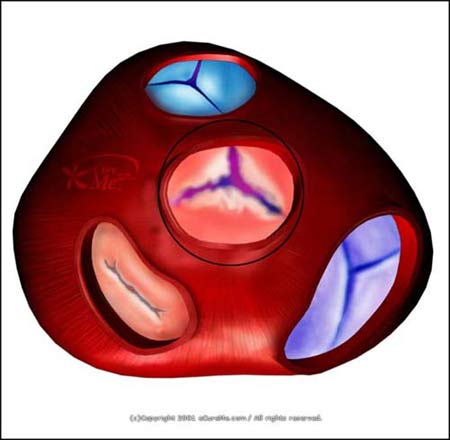
In the afternoon we were a bit quiet, so the SHO took me over to see the 2 patients who are being operated on and whose anaesthatist I am with tomorrow. Both are having heart surgery, so I had a look in their notes and noted the drugs they were on and went to see them so they would know who i was and why I would be in theatre tomorrow (if they care at that point!). Upon coming home and checking the drugs they are on, one patient is on Clopridogel, which is a drug which aims to prevent your blood clotting (an anti-platelet). The BNF and other textbooks recommend stopping it 7-14 days prior to surgery unless it is needed for anti-platelet reasons. So that case may be a little interesting anyway. When I went to meet that patient, who is having an aortic valve replacement, and potentially a CABG - the consent sheet and referral letter said different things! - I had a listen to her chest and the murmur was really loud and obviously diastolic. Even the SHO said it was one of the best she had heard.
Tuesday, July 17, 2007
Elective - day 1
Phew. Today went well - I found the place, with many police outside, which surprised me at first.
My supervisor is very helpful and helped me find scrubs etc and then get sorted. I got to see 3 operations , mostly plastic surgery today and I get to see a variety of different anaesthetic environments this week - Maternity, cardiac Surgery and ICU.
The SpR I spent a large chunk of the day with was very helpful, explaining what they monitored and how, and why some of the values were still normal, even though in an awake person they would be considered very high. he also explained the 3 main classes of drugs used, and how they affect the body and why they affect you and wear off at different rates. He also guided me through the many tubes and masks that are available and some of the situations in which you would use each one and why.
We also got to see a medical emergency. walking through recovery, one of the patients was gasping for breath and making groaning noises - Stridor - which is when the airway is obstructed or narrowed, and the patient can't get enough air into the lungs. this obviously makes them a bit panicky, since they are only just coming round from the operation anyway. The patient was given an injection of a steroid to reduce any inflammation that was blocking the airway, and also inhaled some adrenaline which would achieve the same effect, tough for a much shorter time. Because the cause of the patient's stridor was not known, he was wheeled back round into an anaesthetic room, and had a fibre-optic probe put down his nose to check that there was no obstruction.
Today I also got my access all areas hospital ID card and discovered that the hospital is truly a maze and that you can get from A to B via C,D or E and that the theatre corridor connects them all.
Elective - Day 0
Hmm night before elective and the nerves are kicking in
Oh well I find out what the world of Anaesthetics is like in 8 hours, and I still haven't sorted most of my to do list from yesterday yet.
- Can I find it?
- Will he remember?
- What do I do with money keys phone etc?
- What money will I need for lockers?
- What hours will I be doing?
- Where will I be working?
- Will i have time for revision?
- What do I need to take with me?
Oh well I find out what the world of Anaesthetics is like in 8 hours, and I still haven't sorted most of my to do list from yesterday yet.
Monday, June 4, 2007
The colour of blue, reminds me of you.....
Ok, ok enough of the S-club 7 song lyrics!!
It would seem that a large proportion of my female friends have weird fantasies. Involving NHS property.
Ever since I started telling people that my summer elective would be in anaesthetics and i would be spending the summer in operating theatres, wearing scrubs (I must learn that it has a lower case S!), no fewer than 4 of my friends (all female) have asked me to steal them a set of scrubs to use a pyjamas.
 When I pointed out that if you are so desperate, you can buy them online, they all said "No, they must have 'Hospital property' printed on them". The world is full of some strange people, but if all my friends start appearing wearing blue scrubs, you know my kleptomania got the better of me over the summer.
Personally I blame e4, JD and Elliot. But there must be a reason why guys don;t want to sleep in scrubs?
It would seem that a large proportion of my female friends have weird fantasies. Involving NHS property.
Ever since I started telling people that my summer elective would be in anaesthetics and i would be spending the summer in operating theatres, wearing scrubs (I must learn that it has a lower case S!), no fewer than 4 of my friends (all female) have asked me to steal them a set of scrubs to use a pyjamas.
 When I pointed out that if you are so desperate, you can buy them online, they all said "No, they must have 'Hospital property' printed on them". The world is full of some strange people, but if all my friends start appearing wearing blue scrubs, you know my kleptomania got the better of me over the summer.
Personally I blame e4, JD and Elliot. But there must be a reason why guys don;t want to sleep in scrubs?
Subscribe to:
Posts (Atom)